Wandering and Dementia (Comprehensive Guide)

wandering and dementia

Many people with dementia may at one time have to deal with wandering and dementia.

The Alzheimer’s Association reports that 6 in 10 people who have dementia will wander. This normally happens in the early stages of the illness.

Studies also show that the risk of wandering is usually higher for men than women.

Read on to find out more details about wandering including symptoms, causes, management & prevention strategies, caregiver goals, and planning for emergencies.

Warning Signs for Wandering in Dementia

warning signs for wandering in dementia
There are several symptoms loved ones or caregivers can look out for to know if a person with dementia is at risk of wandering and some of them include:

  • Forgetting how to get to familiar places
  • Taking longer periods to get back home from regular drives or walks
  • Wanting or trying to “go home” even when a person is at home already
  • Talking about fulfilling former obligations like going to the office
  • Pacing, making repetitive movements, or being restless often
  • Asking about the whereabouts of past relatives or friends
  • Having a hard time accessing familiar places in the house like the dining room, bathroom, or bedroom
  • Acting anxious or nervous in public places with crowds such as restaurants or malls
  • Acting as if a person is engaging in a chore or hobby but they are not getting anything done. For instance, a person may be in the kitchen with a pot but they are not cooking anything

Reasons People with Dementia May Wander

reasons people with dementia may wander
The exact causes of wandering are not yet fully understood.

However, there are certain triggers associated with wandering and dementia and some of them include but are not limited to:

Fear or Stress

Individuals with dementia may start to wander as a reaction to feeling nervous in their current environment.

New Environments

People with dementia may feel disoriented or uncertain when they have to adapt to a changed environment like a new home or care center.

Many people may also want to escape from busy or noisy spaces. Wandering may stop once a person gets used to the chances.

Unmet Basic Needs

A person may wander off as they go looking for water, food, or the bathroom. Some people may also want to explore the outdoors and forget the way back home.

Loss of Short-Term Memory

Wandering may be caused by loss of memory. An individual may set off to go visit a friend or go to the shops and then forget where they are going or why.

A person may also forget that their loved one was going out and set off to look for them.

Searching

Affected individuals may get lost while looking for something or someone like a long-lost friend.

Excessive Energy

An individual may also start wandering as a way of using excess energy, which is one of the reasons why patients with dementia walk so much. It may be an indication that the individual needs to exercise more.

Visual-Spatial Issues

Individuals with dementia may get lost even in familiar places because the illness affects the areas of the brain that are responsible for navigation and guidance, even vision.

Expressing Boredom and Loneliness

People with dementia find it more challenging to concentrate on one thing as the illness progresses. Wandering can be one of the ways they keep occupied.

Following Past Routines

Some people will wander off as they try to go back to their former workplaces or grocery stores.

Devices to assist caregivers with monitoring wandering

ProductFeaturesAvailable on Amazon
Bed Alarm for Elderly Dementia PatientsBed Alarm for Elderly Dementia PatientsMotion sensor
Portable pager
Fall prevention
Easy to install
Wireless
Caregiver Pager, Wireless Panic Buttons Elderly Monitoring AssistanceCaregiver Pager, Wireless Panic Buttons Elderly Monitoring AssistanceIntercom
Waterproof
Durable
58 loud chimes
Easy to install
500ft wireless
4pc Security Home Camera4pc Security Home Camera24/7 full HD recording
Enhanced night vision
Video alarm system
AI identification
Home app for family
Cordless Bed Exit Monitoring System AlarmSmart Caregiver Corporation Cordless Bed Exit Monitoring System Alarm with Bed Pressure Sensing PadPrevent falls & wandering
Wireless portable (300ft)
Pressure pad and monitor
Elderly Cellular Medical Alert DeviceElderly Cellular Medical Alert Device| Wearable Panic Button Necklace | Medical Alert Systems for Seniors Fall detection
2-way communication
Waterproof
5 emergency contacts
Lifetime warranty
Elderly Cellular Medical Alert SmartwatchElderly Cellular Medical Alert Device | Medical Alert SmartwatchFall detector
2-way communication
Heart rate, blood pressure, oxygen monitor
Lifetime warranty

Strategies for Preventing and Managing Wandering

strategies for preventing and managing wandering with dementia patients
While chances of wandering are pretty high, there are various prevention and management tips that caregivers can use to help reduce the chances such as:

Visiting a Doctor

When a person with dementia starts to wander, it is advisable to consult a doctor who will conduct a physical check-up.

This helps to identify whether discomfort, pain, or an existing illness is triggering wandering. It may help to discuss any side-effects of medication that the person is taking.

It is best to avoid medication that increases confusion or causes drowsiness and incontinence

Creating Daily Routines

When looking after a person who is battling both wandering and dementia, it is advisable to create a routine the person with the illness follows every day.

This helps to offer structure so that the affected individual is “busy” all day lowering the chances of wandering. Where possible, identify the times of the day or night where the individual is most likely to wander.

This is the best time to plan fun activities or appropriate exercise for the person. It can help reduce agitation, restlessness, and anxiety.

Offer Reassurance

If a person with dementia is feeling abandoned, disoriented, or lost; caregivers should communicate in a reassuring manner.

Focus mostly on validation and exploration. For example, if a person insists that they need to go “home” or to “work” caregivers can tell them something like “It is okay, we will be staying here tonight where we will be safe and can go home or to work in the morning.”

Do not try and correct the person because it can lead to more confusion and agitation.

Meet Basic Needs

Some people with dementia will wander because their basic needs have not been fulfilled. It is; therefore, the responsibility of carers to ensure they meet all their basic needs on time.

This includes making sure they eat well, hydrate, and go to the bathroom when need be.

Avoid Busy Places

This can be anywhere from grocery stores, shopping malls, and other busy avenues. These places can be confusing causing disorientation.

Remove Access to Car Keys

If the person is no longer driving; ensure that car keys are not in sight. This is because persons with dementia do not only wander on foot.

It is easy for individuals to forget that they can no longer drive. If a person can safely drive, it may be best to use a GPS device so that if they get lost, they can be found easily.

Additionally, it is also advisable to keep shoes, hats, coats, and other items that are associated with leaving home out of sight.

Offer Supervision

When taking care of a person with dementia, keep an eye on them especially when visiting new environments so that they do not get lost.

Do not lock the affected individual in a car or house alone.

Beef up Security

There are several options to explore when it comes to this.

For instance, installing door locks that are either high or low so that they are out of the line of sight and not easily accessible by individuals with the illness.

Camouflaging doors by placing removable curtains over doors or painting them a color that matches the surrounding walls can also help.

Investing in devices that signal when windows or doors open can also be helpful. This can be a sophisticated electronic home alarm system or a simple bell placed above the door and window.

This alerts caregivers when people with dementia are attempting to leave the house.

Identification Card

It is also important for the person with dementia to have an identification card on them at all times.

Additionally, they can also wear medical bracelets, or put on clothes that have labels with their information.

Planning For Emergencies

planning for emergencies
When it comes to looking after a person experiencing wandering and dementia, it is important to have a plan in place for emergency situations.

This is because wandering can pose various safety issues particularly in very cold or hot temperatures. Some of the plans that can be put in place include:

  • Having a list of people to contact for help- Store phone numbers where they are easily accessible.
  • Request neighbors, family, and friends to call if they see the person with dementia staying alone.
  • Take close-up photos of affected individuals regularly and have updated medical information that can be given to the police.
  • Create a List of Places an Individual may Wander- These can include places such as former homes, past job locations, former schools, favorite restaurants, and places of worship.
  • Study the Neighbourhood Well- this helps to note down potentially dangerous spots near the house such as open stairwells, water bodies, tunnels, dense foliage, bus stops, and roads with heavy traffic.
  • To be on the safe side, it is best to consider enrolling an individual with a wandering response service.

If a person happens to wander try and stay calm as you begin the start the search and rescue efforts as soon as possible.

In most cases, persons who wander are usually found within one and a half miles of where they disappeared. If the person is not found within the fifteen minutes, file a missing person’s report by immediately calling 911.

Do not forget to let the authorities know that the individual has dementia.

Wandering and Dementia Caregiver Goals

When responding to wandering from persons who have dementia, care goals can be categorized into:

1. Encouraging, maintaining, and supporting choice and mobility enabling the person to move around independently and safely.

2. Assessing and managing the causes of wandering paying close attention to meeting basic needs.

3. Prevent unsafe wandering.

There is still limited research when it comes to wandering and dementia.

However, caregivers can still respond to the new development appropriately to ensure the person with dementia remains safe and happy.

Sundowning And Dementia – A Pattern Of Deterioration?

sundowning and dementia

There can be a pattern of deterioration when it comes to sundowning and dementia.

Some people with dementia normally go through challenging times during the late afternoons or early evenings. This is a condition that is known as sundowning.

It is also known as sundown syndrome or late-day confusion.

This is where a person with dementia may experience big changes like irritability, agitation, confusion, and restlessness that can either start or become worse as the day begins to end.

Everything to Know About Sundowning And Dementia

These usually get better by daybreak. At times, this might continue into the night, affecting how a person sleeps and eventually how they function during the day.

In most cases, sundown syndrome happens to persons who have advanced or mid-stage dementia.

Almost 20% of people who have dementia experience the syndrome.

Sundowning itself is not a disease, but it is a group of symptoms that tend to occur at a specific time of the day affecting persons with dementia.

Even though sundown syndrome is real, it is one of the most misunderstood dementia behaviors. Below we get into more details about sundowning and dementia – a pattern of deterioration?

Possible Causes of Sundowning

possible causes of sundowning
It is still not clear what the exact causes of sundowning are. Studies, however, suggest a few theories that explain what some of the possible causes might be.

One of the most prominent is the changes that happen in the brain, which in turn affect an individual’s “biological clock,” making them confused about the wake and sleep cycles.

It is where a person cannot tell when it is daytime or when it is nighttime.

The problem becomes worse when the clock changes, i.e. when the daylight becomes extended or suddenly gets lost. This often leads to irritability and other sundowning behaviors.

Other factors that may cause this condition include:

  • Pain and discomfort
  • Being overly tired
  • Boredom
  • Depression
  • Thirst, hunger, or other unmet needs
  • More shadows and less light in the house
  • Reactions to frustration cues that exhausted caregivers may showcase at the end of a long day
  • Overstimulation by noisy children, a loud TV or when their caregiver is doing chores around their living space.
  • Changes in the environment: Most people with dementia are attuned to their environment to the extent that they can become distressed when slight or big changes occur. For instance, if a person lives in a nursing home, agitation may come about when there is a shift change. At home, it is easy for the persons with dementia to pick up bad moods from their relatives which often leads to a reaction.
  • Disorientation because of not telling the difference between reality and dreams while sleeping
  • Existence of infections like UTI (urinary tract infection), etc.

Signs of Sundown Syndrome

signs of sundown syndrome
When discussing sundowning and dementia, It is important to pinpoint some of the signs to look out for if you suspect that a person with dementia has late-day confusion.

Some of the most common ones are:

  • Yelling
  • Pacing
  • Mood swings
  • Seeing or hearing non-existent things
  • Arguing
  • Wandering
  • Restlessness
  • Confusion
  • A compelling sense that someone is in the wrong place
  • Rummaging through rooms, or drawers, etc.

When a person is going through some of the above behavioral changes, it is not the time to get into an arguing contest with them.

Some of the tips you can work with to help make the situation a little better include:

  • Approaching the person in a calm way
  • Asking if there is anything the person needs
  • Offering gentle reassurance that everything is under control
  • Reminding what time of the day it is in a kind manner

How to Deal With Sundowning

If you notice that the person with dementia you are caring for has sundowning signs, there are a few steps you can take to cope with the situation such as:

Creating distractions

sundowning and dementia
If an individual becomes excessively agitated, try to take control of the situation by calmly listening to their frustrations and concerns.

Do your best to reassure the person that everything will be fine. You can also create distractions from upsetting or stressful events.

Develop a routine

Setting regular times for meals, waking up, bathing and retiring to bed can help with the situation.

It is also important to try and schedule outings, appointments, and visits during morning hours when a person is likely to feel their best.

Identify triggers

identify triggers
Another way you can help a person going through sundowning is to look for patterns.

Note down the things that may be triggering the condition and go ahead to limit or avoid them.

Avoid or limit things that affect sleep

Persons with dementia should not drink alcohol or smoke. Additionally, you can encourage them to consume bigger meals during breakfast and lunch and make evening meals simple and small.

If a person loves caffeine and sweets, let them take these in the earlier part of the day. Long naps in the afternoon should also be discouraged.

Keep them active

keep them active
Another piece of advice when speaking about sundowning and dementia is to keep the persons with dementia active or busy during the day, something that can promote a good night’s sleep.

Daytime inactivity can result in issues with sleep.

Offering familiarity and comfort

offering familiarity and comfort
People who have dementia appreciate being surrounded by comforting persons, thoughts, and things.

These usually help one to cope with some of the challenging issues that crop up as they are dealing with the illness.

Whether the person is living at home or at an assisted facility, ensure that they have all the items they cherish.

Loved ones should also try and visit them often to keep them company and keep them smiling. This also helps to combat stress a move that can lessen sundowning symptoms.

Reduce demands on the person with dementia

reduce demands on the person with dementia
If a person has late-day confusion, try and make their late afternoons and evenings as stress-free as possible.

It should be a time when they just relax. This includes telling the person to do things that you might think are relaxing, such as taking a bath, listening to music or meditating.

It might be helpful because it means that their brain will not be giving in to the pressures of environmental demands.

Change tone

change tone
The way you talk to a person who is going through sundowning episodes must be addressed when tackling the issue on sundowning and dementia.

You must always use “inside” tonal voices talking soothingly and slowly.

Listen carefully to the response of the person you are caring for to see if you can arrest the source of distress.

If you feel like the individual is comfortable, sit close to them and reach out holding their hand and softly stroke his or her arm.

Enhance security in the home

enhance security in the home
This is especially helpful for those people who tend to wander due to sundown syndrome.

You can keep your loved one safe by putting in place measures like using the right type of window and door locks or installing motion detectors and door sensors so that those around can receive alerts when the person with dementia is on the move.

With this in mind, you need to avoid the use of restraints at all costs.

If the individual needs to pace, you can allow them to do so in a safe environment under your supervision instead of pinning them down a move that can make the situation worse.

Follow a chilled evening routine

follow a chilled evening routine
Routines are not a preserve for daytime when you are dealing with a person with dementia. You can also have one in the evening to help ease the transition process.

Here you can include activities like stroking a pet, reading a book if it is possible, listening to soothing music, etc.

If you are watching TV or listening to the radio, set this to a program that is relatively quiet and calming.

People shouting or loud noises can distress individuals who have dementia.

If the above tips do not generate the results you desire, it may be time to seek help from a professional doctor.

He or she will check out the individual with dementia to offer appropriate solutions.

For instance, the medic might have to change medicines that an individual is taking so that he or she only takes drugs that help in relaxation and do not cause more confusion.

Medicine to Treat Sundowning

medicine to treat sundowning
When dealing with sundowning and dementia, it is okay to be curious about whether any drugs that make these symptoms better.

This is because caregivers at times go through extremely overwhelming sessions where any interpersonal strategies they try do not seem to work.

Prescriptions are available, but a person with dementia should only use this as a matter of last resort. You must try everything else first before you go down the drug route.

A situation where it may be necessary to use medication is where there is a high degree of agitation that is running out of control and the caregiver cannot manage this effectively.

Medicine can help reduce distress so that the person who has dementia gets fast relief from their upset.

Examples of drugs that the doctor can prescribe include antipsychotic medicine which in as much as they can be effective, they can also carry certain risks.

This is why it is important to be very cautious when administering any type of drug to a person undergoing sundowning.

At What Stage of Dementia Does Incontinence Occur?

at what stage of dementia does incontinence occur

At what stage of dementia does incontinence occur? There is no single stage when everyone with dementia becomes incontinent. Continence problems can occur at any stage, although loss of bladder control becomes increasingly common as dementia progresses and is particularly common in the later stages.

Some people never become fully incontinent. Others may begin having occasional accidents much earlier.

Importantly, new or suddenly worsening incontinence should not automatically be assumed to be caused by dementia. Urinary tract infections, constipation, medications and other medical conditions can also cause continence problems and may be treatable.

At What Stage of Dementia Does Incontinence Occur?

The answer varies considerably from one person to another.

According to the NHS, bladder incontinence is common in the later stages of dementia, and some people also experience bowel incontinence.

However, continence problems are not limited to advanced dementia. The Alzheimer’s Society explains that people with dementia can experience difficulties using the toilet for many different reasons as the condition progresses.

A useful way to think about it is:

  • Earlier stages: most people remain independent with toileting, although some may experience urgency, occasional accidents or continence problems caused by another medical condition.
  • Middle stages: memory, communication, mobility and difficulty finding or using the toilet can begin causing more frequent accidents.
  • Later stages: urinary incontinence becomes much more common. Some people also lose bowel control and may require substantial assistance with toileting and personal care.

Dementia does not progress in exactly the same way for everyone, so continence should be assessed according to the individual rather than used alone to determine a particular stage of dementia.

Why Does Dementia Cause Incontinence?

why people with dementia may become incontinent

People with dementia may become incontinent for several reasons, and more than one factor may be involved at the same time.

Dementia Australia explains that dementia can make it difficult for a person to recognize that they need the toilet, remember what to do, find the toilet or use it correctly.

Difficulty Recognizing the Need to Go

As dementia progresses, communication between the brain and the bladder or bowel may become less effective.

A person may not recognize the sensation of a full bladder until the need to urinate becomes urgent.

In later dementia, they may have difficulty recognizing the signal altogether.

Difficulty Finding the Toilet

Memory and spatial awareness problems can make a familiar bathroom surprisingly difficult to locate.

A person may know they need the toilet but forget where it is.

Clear signs, good lighting and keeping the route to the bathroom free from clutter can make a significant difference.

Mobility Problems

A person may recognize the need to use the bathroom but simply be unable to reach it quickly enough.

Arthritis, weakness, balance difficulties and reduced mobility can all contribute to functional incontinence.

Continence Health Australia describes functional incontinence as urine leakage caused by difficulty reaching or using the toilet rather than a problem with the bladder itself.

Difficulty Managing Clothing

Buttons, zippers, belts and complicated clothing can become difficult to manage as cognitive and physical abilities decline.

By the time the person has worked out how to remove their clothing, an accident may have already occurred.

Elastic waistbands and simple clothing can make toileting easier.

Communication Difficulties

As communication becomes more difficult, a person may be unable to explain that they need the toilet.

Caregivers may need to watch for non-verbal signs such as:

  • Fidgeting
  • Pulling at clothing
  • Pacing
  • Restlessness
  • Repeatedly standing and sitting
  • Looking around for the bathroom

Incontinence May Have a Treatable Cause

One of the most important things to understand when asking at what stage of dementia does incontinence occur is that dementia is not always the cause.

The Dementia Australia continence guidance recommends speaking with a doctor so other possible causes can be investigated.

These can include:

  • Urinary tract infections
  • Constipation
  • Prostate enlargement
  • Other bladder or bowel conditions
  • Reduced mobility
  • Medication side effects
  • Changes in fluid intake

Continence Health Australia also recommends investigating new or worsening urinary incontinence rather than assuming that it is simply part of dementia.

Watch for a Sudden Change

A gradual increase in toileting difficulties may occur as dementia progresses.

A sudden change deserves particular attention.

For example, if someone who was normally continent suddenly begins having accidents, becomes more confused or appears unwell, contact their healthcare professional.

A urinary tract infection is one possible cause.

Symptoms can include:

  • Sudden urinary urgency or frequency
  • Pain or burning when urinating
  • Fever
  • New or worsening incontinence
  • A noticeable change in the person’s usual condition or behavior

Not everyone will experience the same symptoms, so significant unexplained changes should be medically assessed.

Types of Incontinence in Dementia

Different forms of urinary incontinence require different approaches.

Urge Incontinence

Urge incontinence involves a sudden, strong need to urinate that may be difficult to control.

The person may know they need the toilet but not have enough time to reach it.

Stress Incontinence

Stress incontinence occurs when pressure on the bladder causes leakage.

For example, a person may leak urine when coughing, laughing, sneezing or exercising.

This is not specifically caused by dementia and can occur in people who do not have dementia.

Functional Incontinence

Functional incontinence is particularly relevant for people with dementia.

The bladder itself may function normally, but cognitive or physical problems prevent the person from reaching and using the toilet successfully.

They may:

  • Forget where the toilet is
  • Fail to recognize the toilet
  • Forget how to remove clothing
  • Be unable to walk there quickly enough
  • Have difficulty communicating their needs

Bowel Incontinence

Bowel or fecal incontinence may also occur, particularly as dementia becomes advanced.

However, constipation can sometimes produce leakage around impacted stool, so new bowel incontinence should also be discussed with a healthcare professional.

Incontinence Products for Dementia

As continence problems increase, the right products can help protect clothing, bedding and skin while allowing the person to retain as much independence and dignity as possible.

ProductFeaturesAvailable on Amazon
Prevail Air Plus Adult DiaperPrevail Air plus Daily BriefSoft & breathable
Ultimate absorbency
Pack of 4 (18 count)
Night & day
Skin smart
Omni-odor guard
Wellness BriefWellness Superio Series BriefsBrand: Unique WellnessFully Absorb up to 2.6L
Wide absorbent core
Resealable landing zone for easy adjustment
White with a nylon based crinkle-free plastic
Value for money
Stays dry for 8+ hours
Award winner/ Featured on Discovery Channel
One Piece Waterproof Snap-on Brief Re-usableOne Piece Waterproof Snap-on Diaper Cover BriefBrand: SalkLightweight
Softness of cloth
100% waterproof
Polyester/urethane outer
Brushed polyester inner
Super-absorbent pad
3-ply inner layer
Waterproof outer layer
Washable
SOSecure Containment Swim BriefSOSecure Containment Swim BriefBrand: Discovery Trekking Outfitters Discreet Swimming Undergarment
Durable Polyurethane Fabric
Fleece Lining
Hook and Loop Closure (Easy)
Elastic Waist & Legs
Machine Washable
Latex Free
Prevail Overnight Bladder Control PadsPrevail Overnight Bladder Control PadsBrand: First QualityFor Women
Dri-Fit cotton enhanced
QUICK WICK Layer and cotton
Odor Guard
Depend Men GuardsDepend Men GuardsBrand: Kimberly ClarkAdhesive strips to hold guard in place
Individually wrapped
Discreet- pocket-sized pouch
Easy carrying and disposal
Contoured design
Cup-shaped protection for men
One size fits most
Medline Incontinence Bed PadsMedline Incontinence Bed PadsUnderpads
50 count
36"X36"
Heavy absorbancy
Polypropylene backing (protects against leakage & resists melting)
Ideal for overnight use
Inspire Washable and Reusable Incontinence Chair or Bed PadsInspire Washable and Reusable Incontinence Chair or Bed PadsWashable/reusable
Solves incontinence problems
Safely absorbs & lock in liquids
Soft & comfortable
Non-irritating
Attends Bariatric 2X-Large UnderwearBariatric 2X-Large UnderwearBrand: AttendsImproved side panels (better comfort & fit)
Acquisition layer
Super absorbent polymer
Tear-away sides (easy removal)
Looks & feels like regular underwear
Bag of 12
Depend Mens Maximum Absorbency UnderwearDepend Mens Maximum Absorbency UnderwearBrand: Kimberly ClarkOutstanding protection
Improved underwear-like fit
Brief-like leg opening
Heavy incontinence
Soft, quiet, breathable material
Conforms to the body
Washable Absorbent Urine Incontinence Underwear for WomenAIRCUTE Washable Absorbent Urine Incontinence Underwear for Women6 layers
High waist
Absorbent & leakproof
Washable
Breathable
Comfortable
Prevail Adult WashclothPrevail Adult WashclothBrand: First Quality
Super strong & soft fabric (12" x 8")
Stay-open & easy-close lid
Press 'N' Pull lid
Super strong soft fabric
Aloe & lanolin
Lid closes tightly

The most suitable product will depend on the person’s mobility, level of incontinence, ability to use the toilet independently and whether protection is required during the day, night or both.

Where possible, seek professional continence advice rather than simply moving immediately to the most absorbent product.

How to Reduce Incontinence and Toilet Accidents

ways to reduce incontinence and toilet accidents in dementia

Even when dementia contributes to incontinence, practical changes can sometimes reduce the number of accidents significantly.

Make the Toilet Easy to Find

A person with dementia may have difficulty remembering where the bathroom is or recognizing the toilet once they get there.

The Alzheimer’s Society recommends making the toilet as easy as possible to find and use.

Helpful changes may include:

  • Putting a clear sign or picture on the toilet door
  • Keeping the bathroom door visible
  • Improving lighting
  • Using night or sensor lights
  • Removing clutter from the route
  • Making the toilet itself easy to recognize

Use Easy-to-Remove Clothing

Replace complicated fastenings with clothing that can be removed quickly.

Elastic waistbands can be especially helpful.

This simple change may prevent accidents when the person understands they need the toilet but has difficulty removing their clothing.

Watch for Non-Verbal Clues

Do not rely entirely on asking, “Do you need the toilet?”

A person with dementia may automatically answer no, forget what the question means or fail to recognize the physical sensation.

Instead, learn the person’s usual signs.

Pacing, pulling at clothing, increased agitation or repeatedly getting up may indicate that they need the toilet.

Create a Dementia Toileting Routine

toileting plan for dementia and incontinence

A regular toileting routine can be helpful, particularly when the person is losing the ability to recognize or communicate the need to go.

Rather than repeatedly asking whether the person needs the toilet, caregivers may gently encourage a bathroom visit at predictable times.

For example:

  • After waking
  • Before leaving the house
  • Before or after meals
  • At regular intervals during the day
  • Before going to bed

Keeping a simple continence or toilet diary for several days can also reveal patterns.

If accidents repeatedly occur around the same time, a caregiver may be able to offer assistance shortly beforehand.

The routine should be adjusted to the person’s individual needs rather than following a rigid schedule.

Do Not Sacrifice Sleep Unnecessarily

Preventing every overnight accident is not always the most important goal.

Repeatedly waking a person during the night may interfere with valuable sleep and may increase confusion or distress.

For some people, appropriate overnight continence products, waterproof bedding and a clear route to the bathroom may be more practical.

Discuss persistent night-time incontinence with a healthcare professional or continence adviser to determine the most appropriate approach.

Keep the Person Well Hydrated

Reducing fluids dramatically may seem like an obvious way to reduce accidents, but it can create other problems.

People with dementia can already be vulnerable to dehydration because they may forget to drink or no longer recognize thirst.

Dementia Australia recommends maintaining adequate fluid intake.

The person’s healthcare professional can advise on appropriate fluid intake if they have other medical conditions that affect how much they should drink.

Caffeine may increase urinary frequency for some people, but dietary or medication changes should be considered in the context of the person’s overall health.

Can Medication Help Incontinence in Dementia?

Medication may sometimes be appropriate, but it depends on the type and cause of the incontinence.

This is particularly important for people with dementia because some medicines used for overactive bladder can have side effects including confusion, constipation, dizziness and an increased risk of falls.

A 2026 review from Continence Health Australia recommends discussing the potential benefits and harms of continence medication with a doctor or pharmacist.

Some existing medications can also contribute to urinary symptoms.

These can include certain diuretics, sedatives and some other medications.

Do not stop or change prescribed medication without discussing it with the person’s doctor or pharmacist.

When Should You Talk to a Doctor?

Speak with the person’s doctor if continence problems are new, worsening or causing difficulty.

Medical advice is particularly important when there is:

  • Sudden onset of incontinence
  • Pain or burning during urination
  • Fever
  • Blood in the urine or stool
  • Severe constipation
  • A significant change in behavior or confusion
  • Difficulty emptying the bladder
  • Repeated falls while trying to reach the toilet
  • Skin irritation or breakdown

A doctor may investigate medical causes and, when appropriate, refer the person to a continence nurse or other specialist.

At What Stage of Dementia Does Incontinence Occur? Closing Summary

There is no exact answer to at what stage of dementia does incontinence occur because every person’s experience is different.

Continence problems can occur in earlier or middle stages, but bladder incontinence becomes increasingly common in later-stage dementia. Some people may eventually experience bowel incontinence as well.

However, an accident does not necessarily mean dementia has suddenly progressed.

Infections, constipation, medications, mobility problems and other conditions can all contribute to incontinence. New or worsening symptoms should therefore be discussed with a healthcare professional.

For people whose continence problems are related to dementia, simple strategies such as clear toilet signs, easy-to-remove clothing, regular toileting routines, appropriate continence products and careful attention to non-verbal cues can make daily life considerably easier.

Above all, continence care should focus on the individual person’s comfort, dignity and remaining independence.

Average Age for Alzheimer’s Disease: Key Facts

Older woman with text reading “Average Age for Alzheimer's Disease”

What is the average age for Alzheimer’s disease? There is no single age at which Alzheimer’s begins, but the vast majority of people who develop the disease are 65 or older.

Age is the greatest known risk factor for Alzheimer’s disease. The likelihood of developing the condition increases substantially as people get older, although Alzheimer’s is not a normal part of aging.

A smaller number of people develop Alzheimer’s before age 65. This is known as younger-onset or early-onset Alzheimer’s disease.

What Is the Average Age for Alzheimer’s Disease?

Most cases of Alzheimer’s disease occur after age 65.

According to the National Institute on Aging, most people with Alzheimer’s develop the disease at age 65 or older, while fewer than 10% develop symptoms before age 65.

There are two broad age-related categories of Alzheimer’s disease: late-onset Alzheimer’s and younger-onset Alzheimer’s.

Late-Onset Alzheimer’s Disease

late-onset Alzheimer's disease in older adults

Late-onset Alzheimer’s is the most common form of the disease and generally refers to Alzheimer’s that develops at age 65 or older.

The risk increases considerably with age.

The 2026 Alzheimer’s Disease Facts and Figures report estimates that 7.4 million Americans aged 65 and older are living with Alzheimer’s dementia.

The percentage of people living with Alzheimer’s rises sharply across older age groups:

  • Ages 65–74: approximately 5.2%
  • Ages 75–84: approximately 13.8%
  • Age 85 and older: approximately 35.8%

About 74% of Americans aged 65 and older who are living with Alzheimer’s are at least 75 years old.

These figures help explain why there is no precise average age for Alzheimer’s disease. The likelihood of developing it continues to increase as people move through their 70s, 80s and beyond.

Importantly, growing older does not mean that someone will inevitably develop Alzheimer’s.

Many people live into their 80s and 90s without developing the disease.

Younger-Onset Alzheimer’s Disease

younger-onset Alzheimer's disease before age 65

Although Alzheimer’s is much more common among older adults, it can also develop before age 65.

This is called younger-onset Alzheimer’s disease, although the term early-onset Alzheimer’s is also widely used.

Many people diagnosed with younger-onset Alzheimer’s are in their 40s or 50s, although rare inherited forms of the disease can cause symptoms even earlier.

Most younger-onset cases are not caused by a single inherited genetic mutation.

However, researchers have identified three rare genes that can directly cause inherited Alzheimer’s disease: APP, PSEN1 and PSEN2.

The National Institute on Aging explains that these genetic variants account for only a small proportion of younger-onset Alzheimer’s cases.

Another gene, APOE, can affect a person’s risk of developing Alzheimer’s, particularly later in life. However, carrying an APOE risk variant does not mean that a person will definitely develop the disease.

How Does Alzheimer’s Risk Change With Age?

how Alzheimer's risk increases with age

When considering the average age for Alzheimer’s disease, it is important to understand that age itself does not directly cause Alzheimer’s.

Instead, aging is associated with biological changes that can make the brain more vulnerable.

Researchers are studying several age-related processes that may contribute to Alzheimer’s disease. These include inflammation, changes to blood vessels, reduced energy production within brain cells, oxidative damage and changes in the way proteins are processed and cleared from the brain.

Over many years, abnormal forms of proteins including beta-amyloid and tau can accumulate in the brain.

These changes may begin long before noticeable memory problems or other symptoms develop.

Other factors can also influence Alzheimer’s risk, including genetics, cardiovascular health, family history and certain lifestyle and environmental factors.

This is why two people of the same age can have very different levels of risk.

At What Age Is Alzheimer’s Usually Diagnosed?

There is no standard age of diagnosis.

Some people are diagnosed soon after symptoms first appear, while others may experience changes in memory and thinking for several years before receiving a diagnosis.

Because late-onset Alzheimer’s occurs after 65 and becomes increasingly common with advancing age, many diagnoses occur during a person’s 70s and 80s.

A diagnosis may involve medical history, physical and neurological examinations, blood tests, brain imaging and assessments of memory and thinking.

You can read more about the types of cognitive tests used when evaluating dementia.

Anyone experiencing persistent changes in memory, thinking, judgment or everyday functioning should discuss them with a qualified healthcare professional rather than assuming they are simply part of getting older.

What Is the Average Age of Death for Alzheimer’s Patients?

There is no single average age of death for people with Alzheimer’s because the disease can be diagnosed at very different ages.

A more useful measure is how long people typically live following a diagnosis.

According to the Alzheimer’s Association, people aged 65 and older live an average of approximately four to eight years after an Alzheimer’s diagnosis, although some people live for as long as 20 years.

Survival varies considerably from one person to another.

Factors such as age at diagnosis, the stage of the disease, general health and other medical conditions can influence life expectancy.

You can read more about average dementia survival and life expectancy.

Average Age for Alzheimer’s Disease: Closing Thoughts

There is no exact average age at which everyone develops Alzheimer’s disease.

The clearest dividing point is age 65. Alzheimer’s developing at or after age 65 is considered late-onset disease, while Alzheimer’s affecting someone younger than 65 is usually described as younger-onset or early-onset Alzheimer’s.

Most people with Alzheimer’s are older adults, and the prevalence rises significantly with age. Current U.S. data shows that approximately 5% of people aged 65–74 have Alzheimer’s dementia compared with more than one-third of those aged 85 and older.

Age is therefore an important risk factor, but Alzheimer’s should never be regarded as an inevitable consequence of growing older.

Understanding the relationship between age and Alzheimer’s can help people recognize when symptoms deserve further investigation and encourage timely medical assessment.

Normal Pressure Hydrocephalus: Is It Reversible?

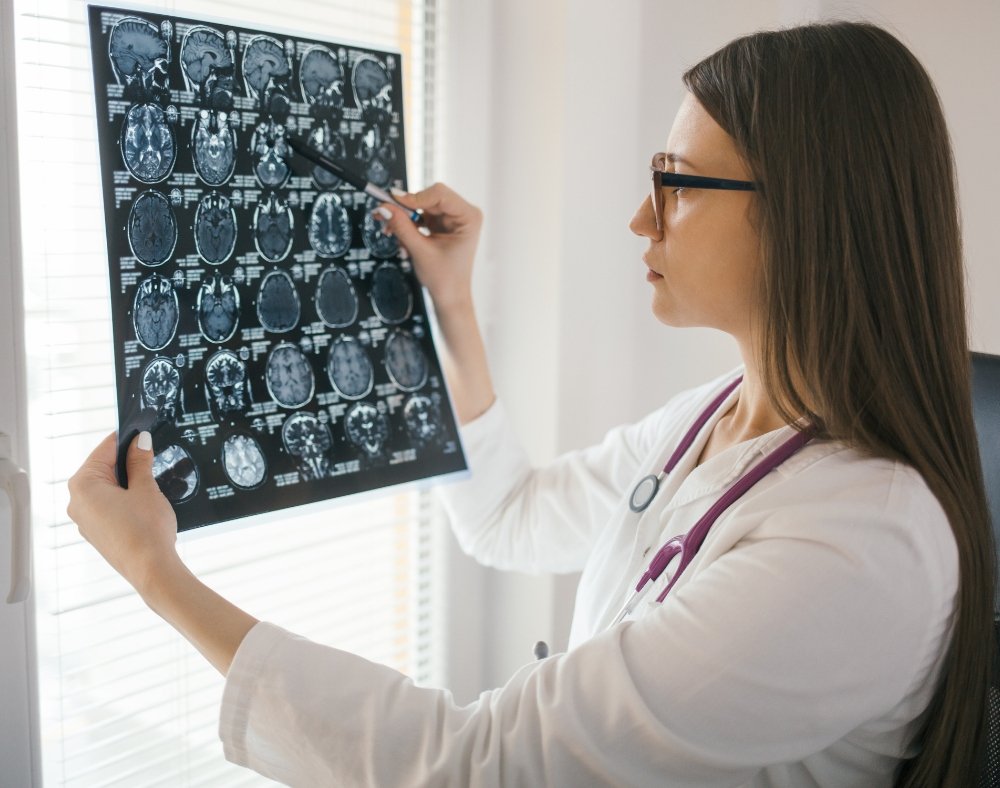
Doctor reviewing a brain scan for normal pressure hydrocephalus

Normal pressure hydrocephalus (NPH) is an important condition to recognise because some of its symptoms can look very similar to dementia, yet they may improve with treatment.

So, is normal pressure hydrocephalus reversible?

The answer is: sometimes, to a significant degree. Treatment can improve walking, thinking and bladder-control problems in some people with NPH. However, improvement varies from person to person, and a complete recovery cannot be guaranteed.

This makes early recognition particularly important. Unlike many progressive causes of dementia, normal pressure hydrocephalus may be treatable when the right patients are identified.

What Is Normal Pressure Hydrocephalus?

The brain contains interconnected spaces called ventricles. These ventricles contain cerebrospinal fluid (CSF), which surrounds and cushions the brain and spinal cord.

Normally, CSF circulates through the brain and is continuously produced and absorbed.

With normal pressure hydrocephalus, too much CSF accumulates within the ventricles. As the ventricles enlarge, they can affect nearby brain tissue and interfere with areas involved in walking, thinking and bladder control.

Despite the name, the pressure of the cerebrospinal fluid may not always be continuously elevated. The condition is called “normal pressure” hydrocephalus because CSF pressure can sometimes appear within a normal range when measured.

NPH occurs most often in adults over the age of 60. Its symptoms can resemble those seen with Alzheimer’s disease, Parkinson’s disease and other neurological conditions, which is one reason diagnosis can be difficult.

The Johns Hopkins Medicine notes that specialised assessment can help distinguish NPH from other disorders with similar symptoms.

What Causes Normal Pressure Hydrocephalus?

possible causes of normal pressure hydrocephalus

In many people, the exact cause of NPH is unknown. This is often referred to as idiopathic normal pressure hydrocephalus.

In other cases, problems with CSF circulation can develop following another condition or event.

Possible causes or associated factors include:

  • Previous bleeding around the brain, including subarachnoid haemorrhage
  • Head injury
  • Brain infection such as meningitis
  • Brain surgery
  • Brain tumours or other structural abnormalities
  • Other conditions that interfere with the normal circulation or absorption of cerebrospinal fluid

A history of one of these conditions does not necessarily mean that someone will develop NPH, and many cases occur without an obvious underlying cause.

What Are the Symptoms of Normal Pressure Hydrocephalus?

symptoms of normal pressure hydrocephalus including walking cognitive and bladder problems

Normal pressure hydrocephalus is classically associated with three main groups of symptoms:

  • Difficulty walking or changes in gait
  • Cognitive or thinking problems
  • Urinary urgency or loss of bladder control

This combination is sometimes referred to as the classic NPH triad.

However, a person does not need to have all three symptoms at the same time. Symptoms may develop gradually, and one may be much more noticeable than the others.

Walking and Balance Problems

Walking difficulty is often one of the earliest and most prominent signs of NPH.

A person may:

  • Walk with shorter steps
  • Have difficulty starting to walk
  • Feel as though their feet are stuck to the floor
  • Shuffle their feet
  • Have difficulty turning
  • Become unsteady
  • Fall more frequently

Because these changes commonly occur in older adults for many other reasons, they can initially be attributed to aging, arthritis or another neurological condition.

Memory and Thinking Changes

NPH can also affect cognition.

Possible changes include:

  • Forgetfulness
  • Slower thinking
  • Difficulty concentrating
  • Trouble planning or organising tasks
  • Difficulty responding to questions
  • Apathy or reduced motivation
  • Confusion
  • Mood changes

These symptoms can resemble Alzheimer’s disease or another form of dementia.

However, the pattern can differ. NPH often produces slowing of thinking, reduced attention and problems with planning and organisation rather than memory loss alone.

Bladder Problems

Changes in bladder control are another common feature.

A person may initially experience a sudden or frequent need to urinate. As the condition progresses, some people develop urinary incontinence.

Bladder problems in an older adult can have many causes, so they should not be assumed to indicate NPH on their own.

Why Is Normal Pressure Hydrocephalus Sometimes Mistaken for Dementia?

NPH can be difficult to diagnose because the people most commonly affected are older adults — the same population in which Alzheimer’s disease, Parkinson’s disease, vascular disease and other causes of cognitive impairment become more common.

The Hydrocephalus Association explains that NPH symptoms can overlap with Alzheimer’s disease, vascular dementia, Parkinson’s disease and several other conditions.

It is also possible for a person to have NPH and another neurological condition at the same time.

For this reason, doctors do not diagnose normal pressure hydrocephalus from symptoms alone.

How Is Normal Pressure Hydrocephalus Diagnosed?

diagnosing NPH using neurological assessment brain imaging and cerebrospinal fluid testing

Diagnosing NPH usually involves several steps rather than one single test.

A neurologist or neurosurgeon may assess:

  • The person’s symptoms and medical history
  • Walking and balance
  • Cognitive function
  • Bladder symptoms
  • Brain imaging
  • The response to temporary removal of cerebrospinal fluid

Brain Imaging

An MRI or CT scan can show whether the brain’s ventricles are enlarged.

Doctors also look at the pattern of enlargement and other features of the brain to determine whether the changes are consistent with NPH or may have another explanation.

Imaging is important, but enlarged ventricles alone are not enough to confirm that NPH is responsible for a person’s symptoms.

Lumbar Puncture or Spinal Tap

A lumbar puncture can be especially useful when assessing whether someone may respond to treatment.

Doctors remove a quantity of cerebrospinal fluid and then reassess symptoms — particularly walking ability.

If walking or another symptom temporarily improves following removal of CSF, this can provide evidence that the person may respond to a permanent shunt.

However, failure to improve after a single lumbar puncture does not always rule out the possibility of benefiting from surgery.

External Lumbar Drainage

In some cases, doctors may use a temporary lumbar drain to remove cerebrospinal fluid over a longer period.

The healthcare team can then repeatedly assess walking, cognition and other symptoms.

Johns Hopkins lists physical assessment, gait evaluation, MRI or CT imaging, spinal tap and temporary CSF drainage among the tests that may be used when diagnosing NPH and assessing possible response to treatment.

Is Normal Pressure Hydrocephalus Reversible?

This is where NPH differs from many other conditions that can cause dementia-like symptoms.

Normal pressure hydrocephalus can be treatable, and some of its symptoms may be partially or substantially reversed.

However, it would be inaccurate to say that every person with NPH will fully recover.

The degree of improvement depends on factors such as:

  • Whether NPH is actually responsible for the symptoms
  • How long the symptoms have been present
  • The severity of the condition
  • Other neurological or medical conditions
  • How the person responds to temporary CSF drainage
  • Whether complications develop following treatment

Johns Hopkins states that complete recovery is possible but is not often seen. Many patients may instead experience meaningful improvement in one or more symptoms following successful treatment.

How Is Normal Pressure Hydrocephalus Treated?

shunt surgery used to treat normal pressure hydrocephalus

The most commonly used treatment for normal pressure hydrocephalus is surgery to implant a shunt.

A shunt is a thin flexible tube that allows excess cerebrospinal fluid to drain away from the brain.

Most commonly, one end of the shunt is placed in a ventricle within the brain. The tubing runs underneath the skin to another part of the body — usually the abdomen — where the excess fluid can be absorbed.

A valve helps regulate the amount of cerebrospinal fluid that drains.

The shunt generally remains in place long term.

Which NPH Symptoms Improve Most After a Shunt?

Improvement varies, but walking and gait problems are often among the symptoms most likely to respond.

Some people also experience improvements in thinking, memory, bladder control or independence with everyday activities.

Cognitive symptoms may be less likely to fully resolve when they have been present for a long time or when another neurological condition, such as Alzheimer’s disease, is also present.

This is another reason why identifying NPH early can be valuable.

Does Shunt Surgery Work for Everyone?

No.

Although many appropriately selected patients improve after shunt surgery, not everyone benefits.

Doctors therefore try to determine who is most likely to respond before recommending an operation.

Improvement after a lumbar puncture or temporary CSF drainage can help predict a favourable response, although no test can predict the outcome with complete certainty.

Shunt surgery also has potential complications.

These can include:

  • Shunt blockage or malfunction
  • Infection
  • Over-drainage or under-drainage of cerebrospinal fluid
  • Bleeding or subdural haematoma
  • The need for adjustment, repair or replacement of the shunt

For this reason, people with a shunt require ongoing medical follow-up.

Why Early Diagnosis Matters

Symptoms of normal pressure hydrocephalus can progress if the condition remains untreated.

Because the disorder can mimic more common causes of cognitive decline, families may initially assume that changes in walking or thinking are simply due to aging or dementia.

A combination of:

  • New or worsening walking difficulty
  • Cognitive changes
  • Urinary urgency or incontinence

should therefore prompt medical assessment, particularly in an older adult.

Recognising NPH is important because it is one of the neurological conditions in which treatment may produce meaningful improvement.

Normal Pressure Hydrocephalus: The Bottom Line

Normal pressure hydrocephalus is potentially treatable, but describing it as completely reversible for everyone would be misleading.

Some people experience substantial improvements following shunt surgery, particularly in walking and mobility. Cognitive and bladder symptoms may also improve, although the response varies considerably.

A complete recovery is possible in some cases but is not guaranteed.

What makes NPH especially important is that its symptoms can resemble dementia, Parkinson’s disease or normal aging. Identifying the condition correctly may therefore give some patients an opportunity for treatment that would otherwise be missed.

If an older person develops a combination of difficulty walking, worsening thinking or memory problems and changes in bladder control, a healthcare professional can assess whether normal pressure hydrocephalus or another condition may be responsible.

Related Articles

Reversible Causes of Dementia

What Is Dementia?

Common Causes of Memory Loss

Cognitive Tests for Dementia

Alzheimer’s Disease

Why Do Dementia Patients Eat So Much? Causes and Helpful Tips

Why do dementia patients eat so much

Why do dementia patients eat so much? There are several possible reasons, including memory loss, changes in appetite and food preferences, anxiety about when the next meal will be, and changes in the parts of the brain that regulate behavior.

Some people with dementia may eat very little, while others may ask for food repeatedly or eat much more than they did previously.

A person may simply forget that they have recently eaten. Others may develop strong preferences for sweet or strongly flavored foods, eat the same foods repeatedly, or become preoccupied with food.

These changes are particularly associated with some forms of dementia, including behavioral variant frontotemporal dementia (bvFTD).

In this article, we look at why overeating can occur, what caregivers can do to help, and when a change in eating habits should be discussed with a healthcare professional.

Why Do Dementia Patients Eat So Much?

There is no single explanation for overeating in dementia.

According to the Alzheimer’s Society, some people with dementia may eat too much or too often because they have forgotten that they recently ate or because they are worried about when their next meal will be.

Dementia can also affect judgment, impulse control, memory, routine and a person’s experience of taste and flavor.

The precise cause will vary from one person to another.

1. Why Do Dementia Patients Eat So Much When They Forget Meals?

why do dementia patients eat so much when they forget recent meals

Memory loss is one of the most straightforward explanations.

A person may finish breakfast and, a short time later, have no memory of eating it.

They may ask when breakfast is being served, look for snacks or prepare another meal because, from their perspective, they genuinely believe they have not eaten.

Some people may also become anxious about food and repeatedly ask when the next meal will be.

Rather than arguing that they have already eaten, reassurance and a predictable meal routine may be more helpful.

2. Frontotemporal Dementia and Compulsive Eating

why do dementia patients eat so much with frontotemporal dementia

Changes in eating behavior can be particularly noticeable in behavioral variant frontotemporal dementia, often abbreviated to bvFTD.

The UCSF Memory and Aging Center notes that overeating is common in bvFTD. Some people develop food fads, repeatedly seek particular foods or develop a strong preference for sweet foods.

This happens because bvFTD affects areas of the brain involved in judgment, inhibition and behavior.

The person may have difficulty controlling the urge to eat even when they are physically full.

For some families, this can become one of the more challenging behavioral symptoms to manage.

3. Changes in Taste and Food Preferences

Dementia can change a person’s relationship with food.

Someone who previously preferred savory meals may suddenly want sweet foods. Another person may begin wanting stronger flavors or eating the same food repeatedly.

The Alzheimer’s Society explains that dementia can affect how much and when someone eats, as well as the foods and flavors they prefer.

Changes in smell, taste and perception can also occur with aging and dementia.

For more information, see our article about food cravings and dementia.

4. Habit, Boredom, Anxiety or Comfort Eating

Eating is not always driven by physical hunger.

A person may repeatedly look for food because they are bored, lonely, restless or anxious.

Food can also become part of a repetitive routine. For example, someone may walk into the kitchen every time they pass it and automatically look for something to eat.

Providing enjoyable activities for a person with dementia, companionship and a predictable daily routine may sometimes reduce repeated food seeking.

The goal is not to stop someone enjoying food, but to understand what may be driving the behavior.

5. Difficulty Recognizing Hunger and Fullness

Dementia can affect the brain’s ability to interpret information and regulate behavior.

Some people may have difficulty recognizing whether they are hungry or full. They may continue eating simply because food remains available.

Others may eat quickly or repeatedly without realizing how much they have consumed.

This is another reason why changes in eating behavior should be considered in the context of the person’s overall dementia symptoms rather than treated simply as a lack of self-control.

6. Medication or Another Health Condition

Not every change in appetite is caused by dementia.

A new medication, medication dose change, diabetes, depression, anxiety, sleep problems and other medical conditions can affect appetite or eating behavior.

A sudden or substantial change in appetite deserves medical attention, particularly if it is accompanied by rapid weight gain or loss, excessive thirst, changes in urination, pain, constipation, difficulty swallowing or other new symptoms.

A doctor can review medications and look for other possible causes.

7. Eating Things That Are Not Food

Occasionally, a person with dementia may attempt to eat items that are not food because they no longer recognize what the object is or what it is used for.

This behavior requires particular attention because items may be toxic, sharp or pose a choking hazard.

If a person repeatedly attempts to eat non-food items, discuss it with their healthcare professional and make potentially dangerous objects less accessible.

How Can You Manage Overeating in Dementia?

practical ways to manage overeating in dementia

When asking why do dementia patients eat so much, it is important to first work out what is driving the behavior.

The most appropriate response to someone who has forgotten breakfast may be different from the response needed for compulsive eating associated with frontotemporal dementia.

Some strategies that may help include:

  • Maintain a predictable meal routine: Regular meals and snacks can provide reassurance about when food will next be available.
  • Avoid arguing: If the person says they have not eaten, repeatedly correcting them may create unnecessary frustration. Reassurance or distraction may work better.
  • Offer nutritious snacks: Fruit, yogurt, vegetables or other appropriate snacks can be kept available if the person frequently wants something to eat.
  • Serve a normal portion in stages: If someone frequently asks for another serving, part of the meal can sometimes be held back and offered a little later.
  • Encourage fluids: Regular access to drinks is important because dehydration is common in older adults and people with dementia.
  • Reduce visual triggers if necessary: If compulsive food seeking is causing a significant health or safety problem, keeping large quantities of tempting foods out of immediate sight may help.
  • Provide meaningful activities: Walking, gardening, music, household activities or social interaction may help when boredom or repetitive behavior contributes to constant food seeking.
  • Keep familiar foods available: Dementia can make unfamiliar meals confusing. Familiar foods may make mealtimes calmer and more enjoyable.

For people with frontotemporal dementia and severe compulsive eating, the National Institute on Aging suggests that caregivers may sometimes need to supervise eating, limit food choices or modify access to food as part of managing behavioral symptoms.

Any restriction should be proportionate to the person’s health and safety needs and preserve their dignity as much as possible.

Healthy Eating Still Matters

healthy eating and nutrition for a person with dementia

A person with dementia does not require a special “dementia diet.”

The Alzheimer’s Association recommends a varied diet that includes vegetables, fruit, whole grains, dairy or suitable alternatives, and sources of protein.

The person’s individual health, weight, medical conditions, medications and nutritional needs should also be considered.

This is particularly important because not everyone with dementia needs to eat less. Many people, especially in later stages, have the opposite problem and may lose weight or struggle to eat enough.

You can read more about this in our related article, Why Do Dementia Patients Stop Eating?

When Should You Speak to a Doctor or Dietitian?

when overeating in dementia may need medical advice

It is worth seeking professional advice if the change in eating behavior is sudden, severe or difficult to manage.

Speak with a healthcare professional if the person:

  • gains or loses a significant amount of weight
  • develops a sudden major increase or decrease in appetite
  • regularly eats until they feel unwell
  • tries to eat non-food items
  • has difficulty chewing or swallowing
  • coughs or chokes while eating
  • has recently started or changed medication
  • has symptoms that could suggest another medical condition
  • eats such a restricted range of foods that nutritional deficiencies are a concern

A doctor can look for medical causes and review medications.

A registered dietitian can also help develop an eating plan if weight gain, weight loss or a very restricted diet is becoming a problem.

Closing Thoughts

There are several possible answers to the question, why do dementia patients eat so much.

For some people, memory loss means they simply forget that they have already eaten. Others become anxious about the next meal, develop new food preferences or use food for comfort or stimulation.

In behavioral variant frontotemporal dementia, overeating and compulsive food seeking can be a particularly prominent symptom.

Rather than assuming the person is simply choosing to overeat, look for the reason behind the behavior.

A predictable routine, nutritious food choices, reassurance, appropriate activities and professional advice when needed can make eating easier to manage while still allowing the person to enjoy food and mealtimes.

References and Further Reading

Alzheimer’s Society. Appetite and dementia.

Alzheimer’s Society. Changes in eating habits and food preference.

Alzheimer’s Association. Food and Eating.

UCSF Memory and Aging Center. Behavioral Variant Frontotemporal Dementia.

National Institute on Aging. How Are Frontotemporal Disorders Treated and Managed?

Dementia And Spicy Foods: Are They Related?

dementia and spicy foods

With the progression of dementia, taste buds weaken, making patients develop strange food cravings, even for extremely spicy foods. But is dementia and spicy foods linked increasing dementia risk?

Are Dementia And Spicy Foods Linked?

The prevalence of dementia is on the rise and numbers are expected to double every 20 years.

It appears when your brain suffers from neurological problems leading to loss of memory and poor judgment.

The decline in memory deteriorates the quality of life in the elderly and, in the long term, reduces cognitive function.

The effects of dementia, and problems happening concurrently with it, are extensive. Moreover, they do not affect the brain only.

Scientists have observed significant alterations in dietary behaviors of people suffering from dementia.

These range from the changes in appetite to unusual food cravings.

How Does Dementia Affect Eating Habits?

how does dementia affect eating habits
Dementia leads to various metabolic and psychological changes in the body. These, coupled with the weakened taste buds, change dietary preferences.

During a research study conducted by the Medical research council, the caregivers of dementia sufferers pointed out a preference for foods that are strong and savory in flavor.

Some of the eating patterns in people with dementia are:

  • Over-eating
  • Binge-eating
  • Decreased appetite
  • Changes in food choices
  • Pica (craving for inappropriate foods)
  • Pica (craving for non-food items e.g. mud)
  • High consumption of sugary and spicy foods

Do People With Dementia Crave Spicy Foods?

do-people with dementia crave spicy foods
The unusual food cravings vary from person to person. Some people crave sweet foods while others incline towards spicy or salty foods.

The reason why the elderly with dementia crave spicy foods are as follows:

1. Dementia Weakens The Taste Buds

The craving is due to the disappearance of taste buds with the progression of the disease.

Humans can identify salty, sweet, sour, bitter, and umami taste.

However, dementia sufferers lose this ability with time. Dementia makes them unable to identify a particular taste as well as differentiate between two different flavors.

This is due to the loss of nerve endings in the tongue.

Since dementia appears with morbid brain conditions, it diminishes the neurological sense responsible for taste.

The elderly cannot feel the tanginess of food so, they ask for a stronger flavor. The same is true for salty foods.

2. Capsaicin Releases Endorphins

Ever wonder why spicy food burns tongue? It is due to the active ingredient present in chili, called capsaicin.

Capsaicin instigates pain receptors in the mouth and tongue, causing a burning sensation.

Due to the activation of these receptors, the brain translates it as a painful experience and floods the body with endorphins.

These are responsible for elevating mood and reducing the painful sensation.

Additionally, dopamine is released which is involved in the reward system of the brain. The result is a euphoric state called “runner’s high”.

Since such neurotransmitters are low in quantity in dementia patients, the body creates a compensatory mechanism.

It generates cravings for foods that cause endorphins to rush.

Is There Any Cultural Relation To Cravings of Spicy Foods?

is dementia and spicy foods linked
Food choices vary immensely throughout the world.

This is also true for the condiments used to prepare local cuisine.

Predictably, the taste buds of natives of each region are adapted to the flavors of their local food seasonings.

Asians consume far more chili and spicy herbs in their meals as compared to westerns.

Therefore, experts think dementia sufferers from the Asian region are more likely to indulge in binge-eating spicy foods.

In such regions, the population develops a habit of using strong spices.

So, they misunderstand their lack of sense of taste in dementia as a bland and flavorless meal.

This results in an excessive intake of chili among the old age population.

Although it is more prominent in areas where spicy cuisine is widespread, westerns are also prone to such cravings.

Their chili usage is minimal but hot sauces and other herbs are still popular in Caucasians and western ethnicities. The proportion may be far lesser but they often enjoy pickles and jalapenos.

A study done in the UK showed that 15% of participants reported a likeness for spicy foods frequently after the onset of dementia.

Do Spicy Foods Increase The Incidence Of Dementia?

do spicy foods increase the incidence of dementia
High spicy food intake may not be as harmful as excessive use of sweets, but it has a deeper relationship with the cause.

Scientists think that chili consumption is linked with an increased risk of dementia.

In Asia, chili is the most frequently used spice. In some regions of China, one in every three adults consumes chili daily.

It has many beneficial impacts on obesity and hypertension due to the presence of capsaicin in it. But there is more to the story.

Considering these properties, capsaicin should reduce the oxidative burden of the brain and enhance cognitive function but evidence proves the opposite.

People who consume more than 50g of chili per day experience a reduction in cognitive function.

The findings also suggested:

  • Twice the risk of self-reported poor memory
  • 56% increase in the incidence of memory decline
  • The low global cognitive score for cognitive function
  • A decline in memory co-efficient with each 10g increase in chili intake
  • Both males and females are equally vulnerable
  • Less marked in overweight individuals
  • Those with normal or low BMI are more prone to dementia due to chili

Apart from these, spicy foods can upset the stomach and lead to long-term gastrointestinal problems.

Considering these findings, it is essential to cut back spicy food consumption in seniors in order to slow the progression of dementia.

How to Manage Spicy Food Cravings in Dementia?

how to manage spicy food cravings in dementia
1. Salty foods can replace spicy foods but they should be used with care as they increase the risk of hypertension in the elderly.

2. The senses of smell and taste are intertwined. So, preparing food with seasoning that can create a delicious aroma helps in managing cravings of spicy food without actually having a spicy meal.

3. Spices, other than chili, and herbs should be incorporated to increase the flavor of the meal.

4. Some naturally occurring spicy foods like jalapenos and pickles used as a seasoning.

Conclusion

The sense of taste diminishes and endorphin production reduces with the progression of dementia.

To overcome these troubles, the elderly often crave spicy foods. They can cause an upset stomach and even worsen dementia with time.

The decline in memory function due to chili is higher in the underweight population. To reduce this possibility, chili should be replaced with better spices and herbs.

Salty meals can be used in a controlled amount but some naturally occurring spicy products like jalapenos and pickles are better substitutes.

Coping with Alzheimer’s and Diarrhea [6 Tips]

alzheimer's and diarrhea

Many elderly persons at some point in their lives may have to deal with Alzheimer’s and diarrhea.

Diarrhea happens when an individual gets three or more watery or unformed stools in 24 hours.

It can be a very tiring time for the affected individual as well as the caregivers.

Can Alzheimer’s cause diarrhea?

There are several reasons a person with Alzheimer’s may experience diarrhea and toilet problems, such as:

1. Medication side effect: Some Alzheimer’s drugs and other medications that a person may be taking could be the cause of diarrhea.
2. Viruses or bacteria: These infections can result in diarrhea.
3. Abdominal Surgery: At times recent surgery especially in the belly area around the gallbladder or intestines can cause diarrhea.
4. Irritable Bowel Syndrome (IBS): Most people who have cramps and diarrhea for no apparent reason may have IBS. This can be caused by stress, lack of exercise, and some food.
5. Malabsorption syndromes: This usually occurs when the body is not getting enough nutrients from the intestines. Examples of these include celiac disease and lactose intolerance.

After knowing some of the reasons persons with Alzheimer’s may get diarrhea, let’s look into some of the symptoms to be on the lookout for when someone has diarrhea.

Symptoms of Diarrhea

Several warning signs may showcase a person has diarrhea, such as:

  • Urgent need to have a bowel movement
  • Bloating
  • Abdominal Cramps or pain
  • Nausea
  • Mucus in stool
  • Bloody stool, chills, or fever are symptoms that can show up if it is bacteria or virus causing the unformed stool

With this in mind, it is time to jump into some of the coping mechanisms that can help deal with a person who has Alzheimer’s and diarrhea.

Increase Fluid Uptake

Alzheimer’s and diarrhea
A person who is going through diarrhea ends up losing a lot of fluids in their body and they are at risk of dehydration.

Caregivers should make sure the person with Alzheimer’s and diarrhea gets plenty to drink.

If an individual can keep liquids down, try and give them water, juice, sports drink, and soda but steer clear from anything that has caffeine or alcohol.

They should drink the fluids even though they are not feeling thirsty.

Apart from water, the other drinks help to put back potassium and sodium that diarrhea deprives the body.

If someone is vomiting, they may not be able to keep the liquids down. This calls for improvising where you feed them small amounts of liquids say one or two tablespoons after every 15 minutes.

If this is not sustainable, you may need to head to the doctors so that the suffering individual can be put on IV fluids.

Offer Easy-to-Digest and Low-Fiber Foods

offer easy to digest and low fiber foods
A person who has diarrhea needs to eat foods that are high in fiber and are easy to digest.

Examples of these include eggs, toast, saltine crackers, rice, chicken, or yogurt.

When giving cooked food make sure they are well-cleaned and cooked so that the foods do not end up making the problem worse.

It is advisable to stay away from heavily seasoned foods, spicy meals, and foods that have high-fat content. Cabbage, beans, raw vegetables, and fruits can also make diarrhea worse.

Avoid Medication

avoid medication
Where necessary, it is usually best to avoid medication when dealing with Alzheimer’s and diarrhea.

This is because diarrhea helps to eliminate viral or bacterial infections.

If a person takes the drugs, the infection may end up staying longer in the body causing more problems. In most cases, diarrhea episodes will last for two days and clear up on their own.

However, if a person must take medication, it is best to seek advice from an expert medic to get a proper prescription.

Keep in mind that the affected individual should stay away from medication if they have a high fever, have been constipated recently, has a swollen belly, or still has diarrhea even after two days.

It is also not advisable for the person to take medication if they have black, tarry stool, blood in the stool, or stool that has a cranberry color.

Use of Supplements

use of supplements
Some supplements can help deal with diarrhea for persons who have dementia.

However, it is important to talk to your doctor before taking anything so that the professional can give you the green light or offer some solid recommendations.

The most common supplements include probiotics that feature normal intestinal bacteria that can help successfully stop the watery stools.

Ensure the Person is as Comfortable as Possible

ensure the person is as comfortable as possible
Diarrhea comes with a lot of discomforts; thus, it is important to make sure that the affected individuals end up feeling as comfortable as possible.

If possible, the person should stay near the washroom so that they can dash in anytime they need to use the toilet.

When mobility is an issue, caregivers may want to consider the use of adult diapers, pads.

Approach this topic with caution because it can be embarrassing for a person who has never used them before.

Change the “briefs” often so that they are not the cause of additional discomfort during the diarrhea period.

Consult a Doctor

consult a doctor
If you try most home remedies and they do not seem to work for Alzheimer’s and diarrhea, it is best to consult a doctor as soon as possible.

The professional will run the necessary tests and offer proper medication.

Other circumstances where it is important to call the doctor include:

  • When a person has had over six watery or unformed stools within two hours
  • If diarrhea happens right after constipation
  • Pale, greasy, and foul-smelling stools
  • Diarrhea that goes on for more than 7 days
  • Diarrhea that is accompanied by a low-grade fever of about 99-101 F (37.2-38.3 °C) that lasts for over 48 hours
  • When there is blood in the stool
  • If vomiting is accompanied by diarrhea

Naturally, a person who has diarrhea may not want to walk into the doctor’s office.

At this point, you may want to consider the services of mobile healthcare professionals.

The experts will travel to the patient and offer home treatment that many persons with Alzheimer’s and diarrhea may prefer.

Migraine and Dementia: Is There a Link?

migraine and dementia

Research looking into the link between migraine and dementia reveals that migraines are among the top dementia risk-factors.

Migraines are a neurological disease that involves repetitive and severe headaches as well as other symptoms.

In some cases, there may be an aura which is a sensory change before the headache occurs. Migraines are not your typical headaches.

They can last for days and can affect an individual’s daily life including their ability to study or work.

The Migraine Research Foundation reports that the disease affects one billion people across the globe.

That makes it the 3rd most widespread disease in the world.

Are Migraines and Dementia Closely Related?

Dementia on the other hand is not a specific disease but a group of conditions that are characterized by impairment of brain functions like judgment and memory loss.

One of the reasons why researchers were interested in studying dementia and migraines is because both are common neurological diseases.

While dementia mostly affects seniors, migraines usually affect people of all ages.

One of the studies that support the idea that there is an association between migraine and dementia was published in the International Journal of Geriatric Psychiatry.

It explains that researchers talked to 679 seniors asking them about their migraine history. More than half of this group were women and none had a history of cognitive problems.

Are migraine sufferers more likely to develop one form of dementia?

are migraine sufferers more likely to develop one form of dementia
The average age of the subjects was 76. The experts pursued elderly individuals for 5 years and discovered that 51 of them had a positive dementia diagnosis.

Considering factors such as age and education, the researchers found that individuals with Alzheimer’s disease (AD) were over four times more likely to have had migraine attacks.

AD is one of the most common forms of dementia.

Suzanne L. Tyas a senior author of the study said that persons with migraines history were three times more likely to develop a kind of dementia and four times more as likely to develop Alzheimer’s.

The study, however, did not find a link between migraines and vascular dementia.

What affects migraines?

migraine and dementia
According to Rebecca Edelmaye, director of scientific engagement at the Alzheimer’s Association, the link between migraine and dementia is advanced by the fact that migraines affect the lifestyle decisions of a person.

This includes not eating a healthy diet, poor sleep, reduced social/cognitive stimulation, and not being active.

These factors have very much in common with those known to increase the risk of dementia.

Previous research had found connections between dementia risk and migraines. Scientists have, however, not yet pinpointed the exact link between the two diseases.

Many suspect that it has a lot to do with vascular risk factors like diabetes and hypertension. On record, these are potential dementia risk factors.

Research also reveals that long-term migraines can alter the structure of the brain resulting in some destructive effects.

A study published in Neurology in 2013 examined the contribution of migraines to structural changes in the brain including volumetric changes in white and gray matter, white matter abnormalities, and infract-like lesions.

Experts in this study were looking for solid evidence and a better understanding of the relationship between migraine and dementia.

Implications of the Studies

implications of the studies
There are a couple of things that come up after the discovery that there is a link between migraine and dementia.

One of them is the fact that the research can help medics predict better the people who are at risk of this neurodegenerative disease.

This might also lead to early detection of the disease. This is an essential part of treatment according to the professionals.

Early detection is helpful because it means that affected individuals can start treatment as soon as possible. It can, in turn, enhance the effectiveness of the treatment therapies.

This can also empower persons with the illness and their loved ones to make the proper decisions at the right time.

There is also a chance that future research will better explain how migraines affect Alzheimer’s and other forms of dementia as well as how to ease the risk.

Stroke and Dementia: Is There A Link?

stroke and dementia

Several studies confirm that there is a link between stroke and dementia.

A stroke occurs when brain cells are damaged or die-off because the flow of blood to the organ is interrupted.

This kind of damage can lead to the development of dementia because it results in problems with thinking and memory.

Dementia is a group of symptoms that result in cognitive decline.

This includes problems with communication, memory, and concentration.

Statistics indicate that having a stroke doubles the risk of developing dementia.

Understanding Stroke and Dementia

The conclusion was made after a large-scale study led by The University of Exeter Medical School. Researchers analyzed data on stroke and dementia risk from over three million people from across the globe.

The experts were building on research that has been previously done but had not quantified the extent that stroke increases the risk of dementia.

The research analyzed 36 studies where 1.9 million subjects had a history of stroke.

They went ahead and also examined twelve more studies where the participants had a recent stroke during the period of the research adding 1.3 million people.

Stroke increases the risk of dementia by 70%

stroke increases the risk of dementia by 70%
Dr. ILianna Lourida who was part of the study from the university said that they discovered that a history of stroke increases the risk of dementia by about 70%.

Moreover, recent strokes increase the risk by more than double.

The link between dementia and stroke was prevalent even after the experts took into account other dementia risk factors like diabetes, cardiovascular disease, and blood pressure.

Findings from this study released strong evidence that having a stroke increases dementia risk significantly.

This was important given how common dementia and stroke are.

World Health Organization reports that 50 million people around the world have dementia and the number will continue to rise significantly.

Meanwhile, 15 million individuals experience strokes yearly.

The study on stroke and dementia is also useful because it can help with the prevention or treatment of dementia.

Dr. David Llewellyn who hails from the University of Exeter Medical School believes that about 1/3rd of the cases of dementia are preventable.

He reckons that protecting the supply of blood to the brain might help to reduce dementia cases.

The research was published in Alzheimer’s & Dementia: The Journal of The Alzheimer’s Association one of the top dementia journals.

What Type of Dementia are People with Stroke Likely to Get?

what type of dementia are people with stroke likely to get
When talking about stroke and dementia, it is important to note that a majority of people who suffer from stroke will end up developing vascular dementia.

This is one of the most common dementia types.

It is not to say that every person who has a stroke will end up with vascular dementia.

The risk may also depend on sex, age, family history, and severity and location of the stroke.

In addition to damaged brain cells, vascular dementia can also develop after an individual experiences a series of silent strokes.

These usually cause small areas of damage in the brain.

They are known as silent strokes because in most cases, the strokes are usually so small that a person may not even know when they are happening.

Worth mentioning is that it is possible to confuse vascular dementia with the effects of stroke.

Both medical conditions can cause issues with memory, mood, and thinking.

If a person with stroke experiences these problems and they do not improve but seem to get worse, it could be an indication that they have vascular dementia.

If caused by a single stroke, the symptoms of vascular dementia can appear suddenly.

They tend to appear gradually if the symptoms are caused by silent strokes. In the absence of dementia, these symptoms will improve after some time.

Experts also believe that stroke can cause dementia at any age. As people grow older, their risk of stroke and dementia increases.

Nowadays, however, stroke risk factors are increasing even for younger adults.

The same case applies to dementia where individuals can start developing the neurodegenerative disease in their 40’s or younger.